
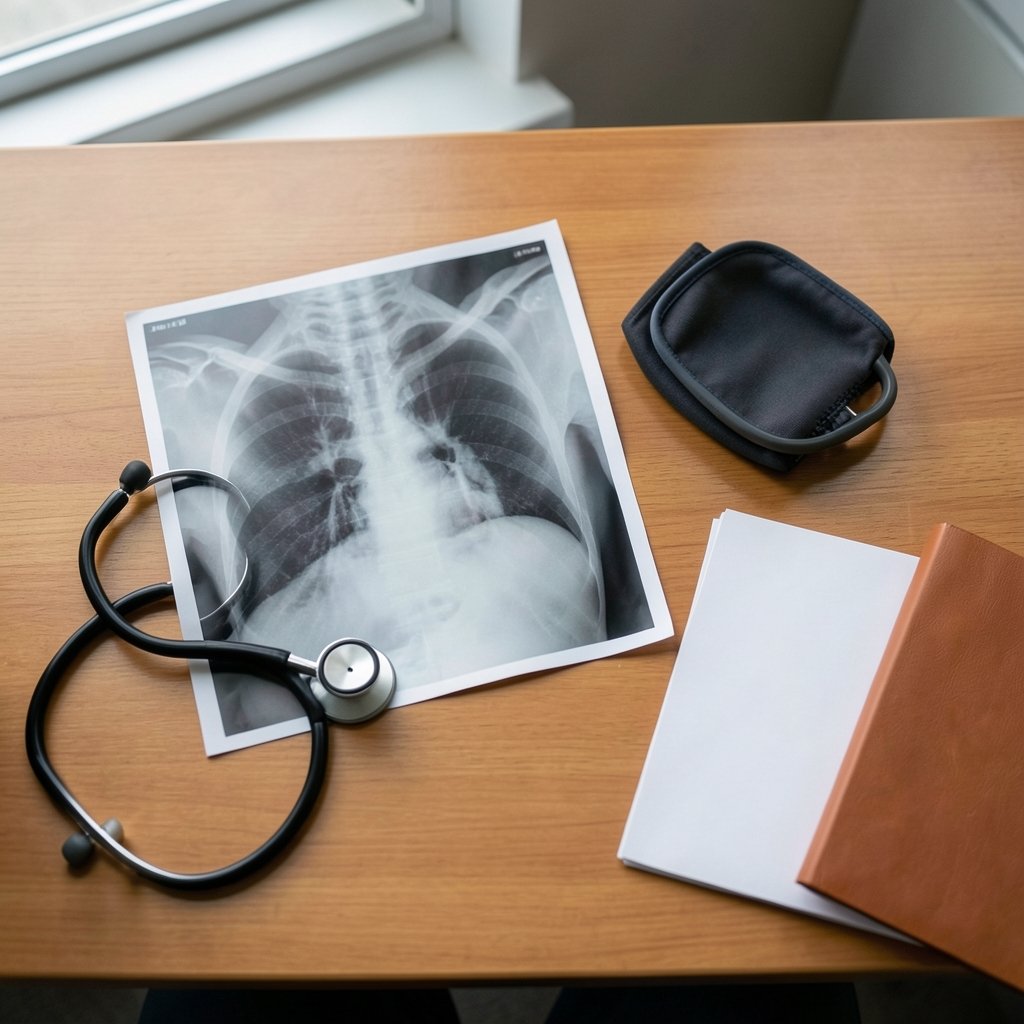
What does it actually mean when a doctor says someone has an “enlarged heart”? The phrase sounds alarming, and it should get attention, but it is also one of the most misunderstood findings in medicine. An enlarged heart is not a disease in itself. It is a physical sign, like a fever or a swollen ankle, that points to something else going on inside the body. Some causes are serious and need treatment. Others are harmless, including a type of enlargement that shows up in healthy endurance athletes.
This guide walks through what cardiomegaly means, how the two main patterns differ, which tests confirm it, what can be done about it, and the mistakes people make when they read a chest X-ray report on their own.
What “Enlarged Heart” Actually Means
Cardiomegaly is the medical term for a heart that is larger than expected. Doctors usually first notice it on a chest X-ray, where they compare the width of the heart shadow to the width of the inside of the chest. A ratio above roughly 0.5 is often flagged as enlarged.
That 0.5 cutoff is worth treating with caution. It is a long-standing screening convention, not a hard diagnostic rule. It misses some cases and flags others that turn out fine, especially depending on how the X-ray was taken and how deeply the person breathed in. Modern practice leans on echocardiography, which shows the heart’s chambers, wall thickness, and pumping function directly.
The key idea to hold onto: an enlarged heart is a finding, not a final answer. The real question is always why the heart got bigger.
The Two Patterns: Dilation vs. Hypertrophy
Not all enlargement looks the same, and the difference shapes everything about treatment. Cardiologists split it into two broad patterns.
| Feature | Dilation | Hypertrophy |
|---|---|---|
| What happens | Chambers stretch and enlarge; walls may thin | Walls thicken; chamber size may stay normal or shrink |
| Typical trigger | Volume overload, weakened muscle, valve leakage | Pressure overload, such as high blood pressure or a narrowed aortic valve |
| Pumping effect | Often weaker contraction | Stiff, thick muscle that fills less easily |
| Common example | Dilated cardiomyopathy | Hypertensive heart disease |
Both patterns can coexist, and both can progress. In dilation, the heart muscle weakens and the chambers balloon as the heart tries to keep up with demand. In hypertrophy, the muscle bulks up against resistance, much like a bicep growing from repeated heavy lifting.
Why the Heart Thickens in the First Place
Hypertrophy is an adaptive response, not random damage. When the heart faces constant pressure, its wall thickens to reduce the stress on the muscle fibers. This follows a principle of physics known as Laplace’s law: a thicker wall lowers the tension each fiber must bear. (What is a large language model)
The trade-off is real. A thick wall is strong, but it is also stiff. Stiff muscle relaxes poorly between beats, so the heart fills with less blood. Over years, that stiffness can contribute to heart failure even when the pumping fraction looks normal.
What Causes an Enlarged Heart?
The list of causes is long, which is exactly why the finding needs a workup rather than a guess. Common drivers include:
- High blood pressure, the most frequent culprit behind wall thickening
- Coronary artery disease, which can weaken the muscle after a heart attack
- Heart valve disease, such as a leaky mitral valve or a narrowed aortic valve
- Cardiomyopathy, a primary disease of the heart muscle
- Arrhythmias, especially fast, persistent rhythms that tire the heart
- Thyroid disease, anemia, and other systemic conditions that force the heart to work harder
- Pregnancy, where blood volume rises substantially for months
Viral infections, heavy alcohol use, and some medications can also play a role in certain cases. The pattern matters: a young person with severe dilation after a flu-like illness tells a different story than an older adult with decades of uncontrolled blood pressure.
Symptoms People Actually Notice
Many people with mild enlargement feel nothing at all. When symptoms do appear, they tend to reflect the heart struggling to keep up:
- Shortness of breath, especially with exertion or when lying flat
- Swelling in the legs, ankles, or feet
- Fatigue that seems out of proportion to activity
- A racing, fluttering, or pounding heartbeat
- Dizziness or fainting
- A persistent cough, sometimes worse at night
These symptoms are vague on their own. Breathlessness after climbing stairs could be poor fitness, asthma, anemia, or a heart problem. That overlap is why testing matters more than symptom-spotting alone.
How Doctors Confirm and Measure It
An X-ray hint is only the start. A typical workup moves through several steps.
- History and physical exam. Blood pressure, heart sounds, lung sounds, and swelling in the legs all provide clues.
- Electrocardiogram (ECG). A quick electrical snapshot that can show thickening, rhythm problems, or prior damage.
- Echocardiogram. The central test. Ultrasound shows chamber size, wall thickness, valve function, and the ejection fraction, which estimates how much blood the heart pumps per beat.
- Blood tests. These screen for anemia, thyroid problems, kidney function, and markers of heart strain.
- Advanced imaging when needed. Cardiac MRI can characterize the muscle tissue itself, and stress testing looks for blocked arteries.
The ejection fraction deserves a note. It is the percentage of blood in the left ventricle that gets pumped out with each beat. A normal value is generally above 50 to 55 percent. Heart failure with reduced ejection fraction is defined as 40 percent or lower. When the left ventricle is enlarged and poorly contracting, that combination is a hallmark of dilated cardiomyopathy.
The Athlete’s Heart Exception
Regular endurance training genuinely enlarges the heart, and that is not a problem. Runners, cyclists, swimmers, and rowers often develop what sports cardiologists call athlete’s heart: mild chamber enlargement with thick but efficient walls and excellent pumping function.
The challenge is telling this benign adaptation apart from a real disease like hypertrophic cardiomyopathy, which can be dangerous. Clues that point toward a healthy athlete’s heart include a very high exercise capacity, normal relaxation on imaging, and changes that reverse with detraining. Clues that raise concern include symptoms like fainting during exercise, a family history of sudden cardiac death, or abnormal ECG patterns. This is exactly the kind of judgment call that should be made by a cardiologist, not by comparing scan results online.
Can an Enlarged Heart Go Back to Normal?
Sometimes, yes. Reversibility depends heavily on the cause and how long it has been present.
When high blood pressure is the driver, bringing it under control can reduce wall thickness over months. When a faulty valve is repaired or replaced, the overload disappears and the heart can remodel back toward normal. When a fast arrhythmia is treated, a tired heart may recover substantially.
When the enlargement comes from long-standing scarring, called fibrosis, full reversal is much less likely. Scar tissue does not behave like healthy muscle. This is the practical reason early detection matters: the heart has more room to recover before permanent changes set in.
Practical Tips and Common Mistakes
A few habits separate people who manage this well from those who get blindsided.
Do not panic at the word “enlarged” on a radiology report. X-ray reports are screening tools, and a mildly prominent heart shadow is often a technical artifact. Get the echocardiogram before assuming the worst.
Do not dismiss it either. The opposite mistake is common: someone feels fine, so they skip the follow-up. Enlargement can progress silently for years before symptoms appear.
Track blood pressure at home. Home readings, taken correctly with a validated cuff and a rested arm, give a far better picture than a single clinic measurement. Many cases of hypertensive heart disease trace back to blood pressure that was never controlled.
Bring a medication list to appointments. Some drugs and supplements affect heart function or interact with treatment. Details matter.
Ask for the numbers. Request the actual ejection fraction, chamber dimensions, and wall thickness. Knowing the trend over time tells a story that a single word like “enlarged” cannot.
Treat sleep apnea seriously. Untreated breathing pauses during sleep strain the heart and raise blood pressure, and treating them can help the heart over time.
How Enlargement Connects to Heart Failure
An enlarged, weak left ventricle is one of the strongest structural signals of heart failure, a condition where the heart cannot deliver enough blood to meet the body’s needs. The link runs both ways: heart failure can cause the heart to enlarge, and enlargement can push a heart toward failure.
Treatment for heart failure with reduced ejection fraction has improved dramatically. Modern regimens combine several classes of medication that work together to ease the heart’s workload and improve survival. Devices such as implantable defibrillators or pacing systems help selected patients. The takeaway is not that heart failure is mild, but that an enlarged heart is often a condition to manage actively for years, not a sentence. (Small language models vs large language models)
When to Seek Care
Anyone with chest pain, fainting, or sudden severe breathlessness should get emergency help. For less urgent concerns, a prompt appointment makes sense for:
- New or worsening shortness of breath with activity
- Swelling in the legs that does not settle overnight
- A heartbeat that feels fast, irregular, or pounding
- A family history of cardiomyopathy or sudden cardiac death
- A chest X-ray report that mentions an enlarged heart
Conclusion
An enlarged heart is best understood as the body sending a message. Sometimes the message is about pressure, like years of high blood pressure quietly thickening the muscle. Sometimes it is about a weak pump, a leaky valve, or a rhythm that never lets the heart rest. And sometimes it is simply the signature of a well-trained athlete’s heart doing its job.
The useful response is neither fear nor dismissal. It is a clear-eyed workup: an echocardiogram, a blood pressure check, blood tests, and a conversation about what the numbers actually show. Cardiomegaly is common, the causes are treatable in many cases, and some enlargement reverses once the underlying problem is addressed. The people who do best are usually the ones who ask for the details, follow up on the imaging, and treat the cause rather than the label.
Frequently Asked Questions
Is an enlarged heart always dangerous?
No. Some enlargement is benign, including the physiological changes seen in endurance athletes. The risk depends entirely on the cause, the pattern of enlargement, and how well the heart is pumping. That is why the finding needs evaluation rather than assumption in either direction. (Raid 5 vs raid 6 nas rebuild risk large drives)
Can an enlarged heart return to normal size?
Sometimes. When the cause is corrected, such as controlling blood pressure, repairing a valve, or treating a fast rhythm, the heart can remodel and shrink over months. Long-standing scarring makes full reversal less likely, which is why early detection gives the best odds.
What is the difference between dilation and hypertrophy?
Dilation means the chambers stretch and the walls may thin, often from a weakened muscle or volume overload. Hypertrophy means the walls thicken, usually from pressure overload such as high blood pressure. The two can occur together, and they lead to different treatment priorities.
Does an enlarged heart always mean heart failure?
No. Enlargement is a structural sign, and heart failure is a clinical syndrome. A person can have an enlarged heart with normal pumping function, and a person can have heart failure with a normal-sized heart. Doctors use the ejection fraction and symptoms together to sort this out.
What test confirms an enlarged heart?
Echocardiography is the standard test. It measures chamber size, wall thickness, valve function, and ejection fraction in real time. A chest X-ray may raise the question first, but the ultrasound answers it.
Can exercise make an enlarged heart worse?
It depends on the cause. In a healthy athlete’s heart, training is not harmful. In someone with a weakened or thickened heart from disease, exercise recommendations should come from a cardiologist, since the right amount and type of activity vary widely from case to case.



